-
-
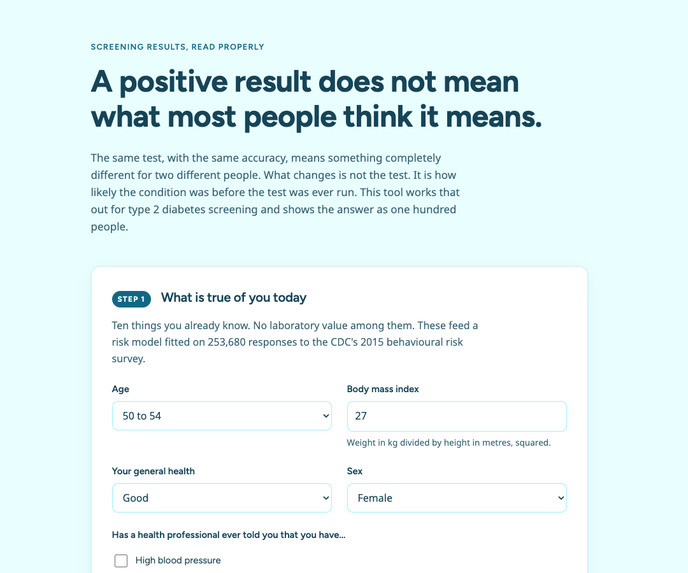
Step 1: ten answers you already know, with no laboratory value, set your risk before the test.
-
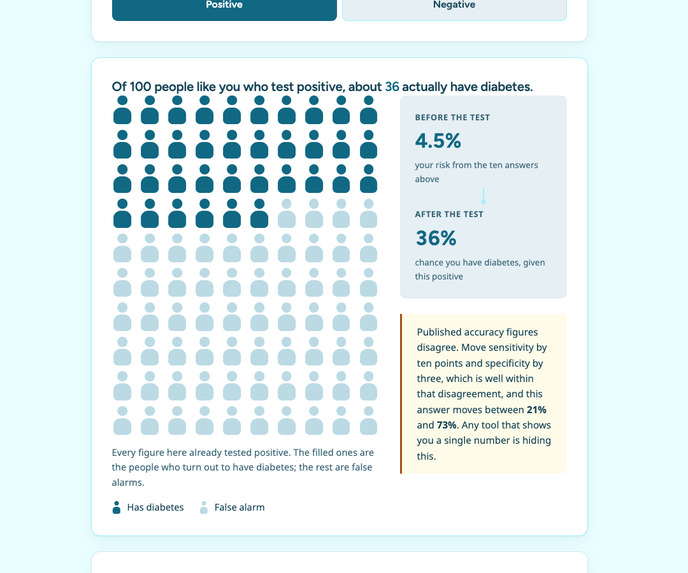
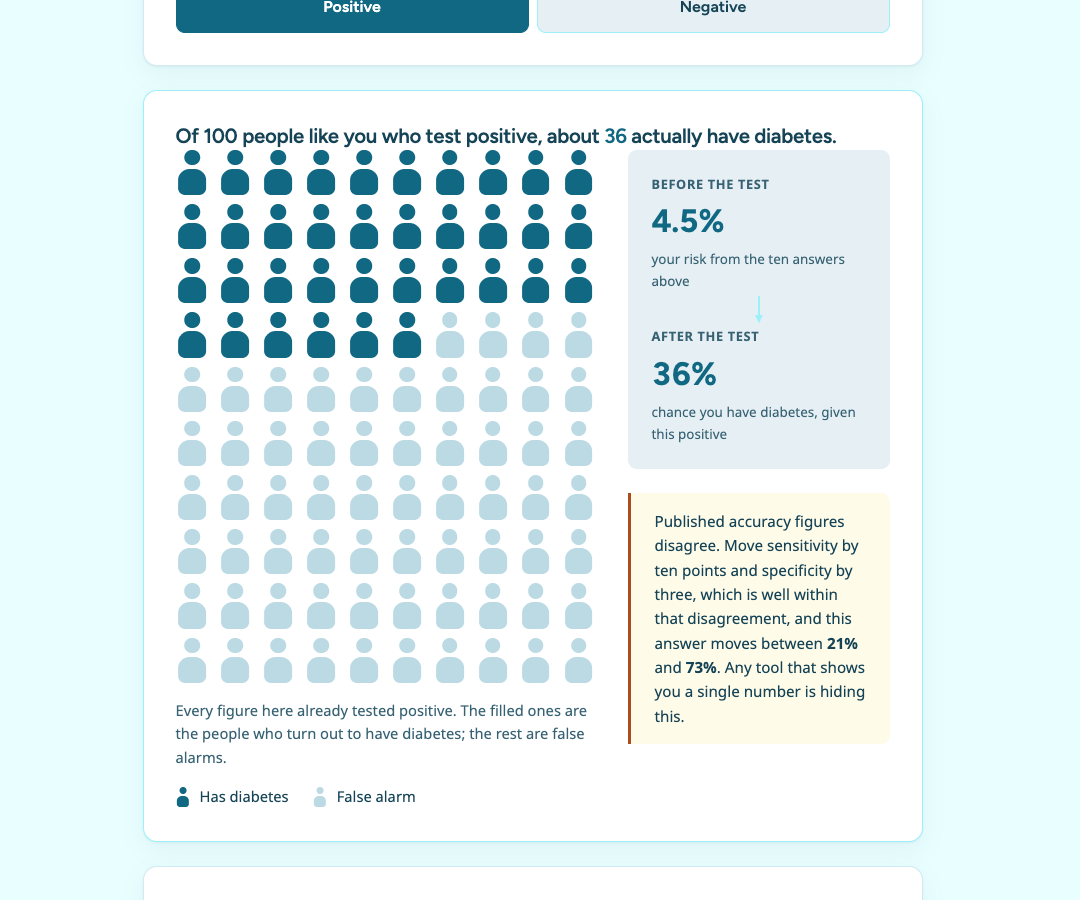
Of 100 people like you who test positive, about 36 actually have diabetes, drawn as one hundred figures.
-
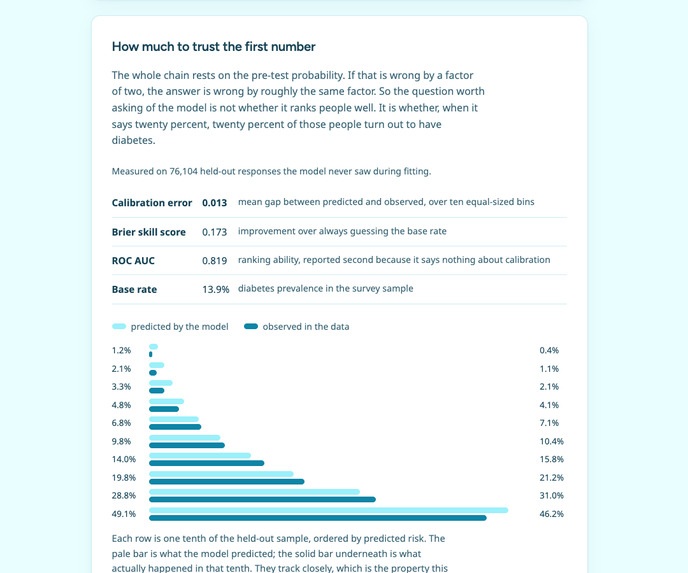
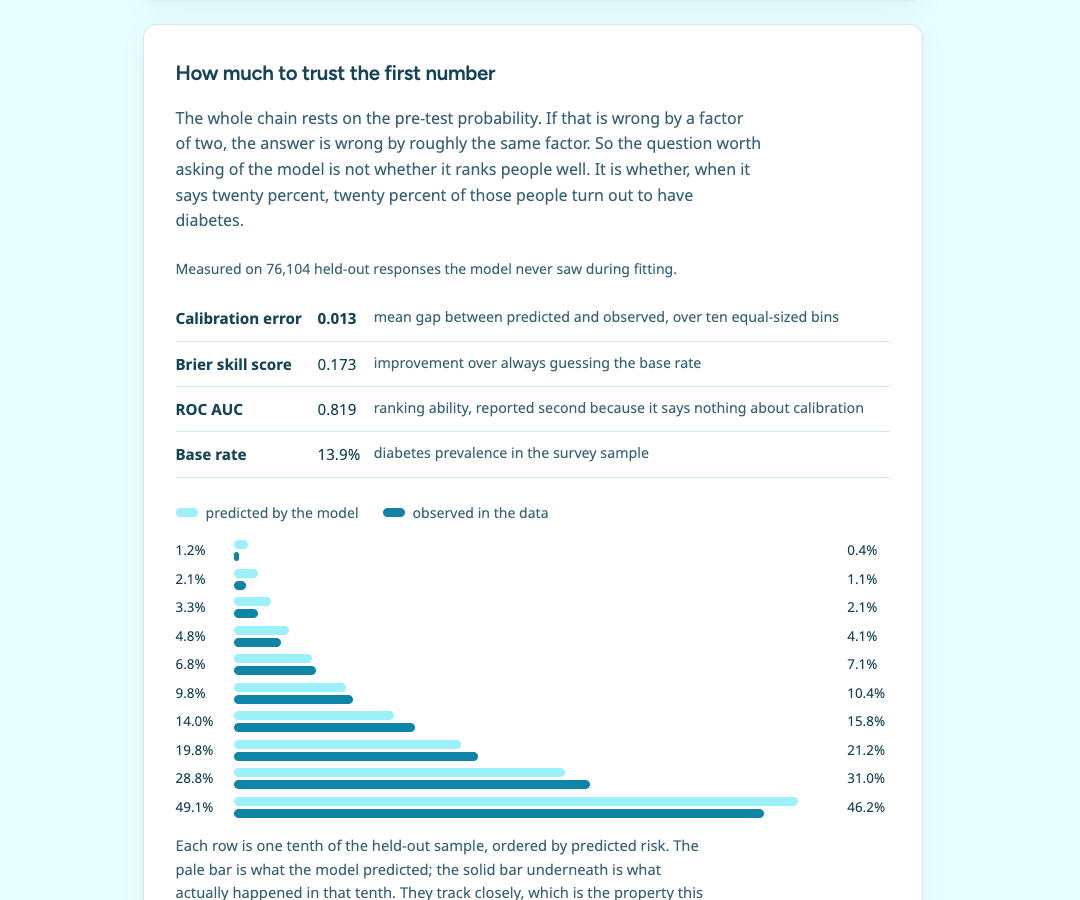
Calibration on 76,104 held-out responses is reported first; ROC AUC comes second.
Inspiration
There is a famous set of studies in which clinicians were given a screening scenario: a rare condition, a decent test, a positive result. Most estimated the chance of disease at 70 to 90 percent. The correct answer was under 10. The gap between what a positive result feels like and what it actually means is a well-documented problem in health communication, and it affects patients and professionals alike. Reading a result needs two numbers together: the risk before the test and the accuracy of the test. This tool combines them for one person rather than for a population.
What it does
You enter ten things you already know about yourself, with no laboratory value among them: age band, BMI, sex, general health, diagnosed high blood pressure or cholesterol, heart disease history, activity, mobility and smoking history. A model turns that into your pre-test probability of type 2 diabetes.
Then you pick a screening test (HbA1c, fasting glucose or a random glucose screen), keep or adjust its sensitivity and specificity, and choose the result you are holding: positive or negative.
The answer comes back as one hundred people. For a 50-year-old woman with BMI 27 and nothing diagnosed, a positive HbA1c means that about 36 of 100 people like her actually have diabetes; 64 are false alarms. For a 70-year-old with BMI 34, high blood pressure and high cholesterol, the same positive result means 92 of 100.
Switch to a negative result and the figures show who the test misses. For the same 50-year-old woman, about 2 of 100 people like her who test negative still have diabetes. The default HbA1c threshold catches only about half of true cases, so about half of the people who do have diabetes are among those it clears.
How we built it
The pre-test model is a logistic regression fitted with scikit-learn on the CDC's 2015 Behavioral Risk Factor Surveillance System sample, 253,680 responses (UCI Machine Learning Repository, id 891). Its coefficients are exported into the page, so the app is three static files: no build step, no backend, no network call and nothing to install.
The result is rendered as a 100-person icon array drawn in pure CSS. People read natural frequencies more accurately than percentages, so the answer is drawn before it is stated.
For this use case, calibration matters more than ranking, and the app reports it first. If the pre-test probability is off by a factor of two, the final answer is off by roughly the same factor. On 76,104 held-out responses the model never saw, the mean calibration error is 0.013 across ten risk bins, and the full predicted-versus-observed table is shown in the app. ROC AUC is 0.819 and is listed second on purpose.
Challenges we ran into
The hardest decision was what not to claim. Published sensitivity and specificity for the same test differ between studies and populations, and a tool that silently picks one value hides that disagreement. Both values stay adjustable, and the app shows how far the answer moves across a plausible range: the 36% example above moves between 21% and 73%. Showing that range without making the tool feel useless took the most design iterations.
Accomplishments that we're proud of
The model is well calibrated on held-out data, the property this use case depends on most. The demo is a static page that runs in any browser, and a single training script that fetches the public dataset reproduces the model.
What we learned
A negative result feels definitive even when the test misses many true cases, and a positive one feels more certain than it is. Showing one hundred small figures explained this better than any paragraph we tried.
What's next for One Hundred People Like You
More conditions and tests, since the same calculation applies to any screening test with published sensitivity and specificity. A printable one-page summary a person could bring to an appointment. And validation against a non-US cohort, which the limits section currently lists as missing.
