



Inspiration
Clinicians spend 2+ hours per complex patient case searching literature, cross-referencing lab values against treatment protocols, and writing structured briefs. Most existing AI tools either hallucinate clinical recommendations or cost $50,000+ per year. There is no open, inspectable, evidence-grounded pipeline that any clinic can run.
I built ClinicalBrief AI based on a research publication on adaptive health orchestration to prove that a fully agentic, source-cited, confidence-gated clinical intelligence pipeline can be built on open infrastructure — in n8n, without a single line of server code.
What it does
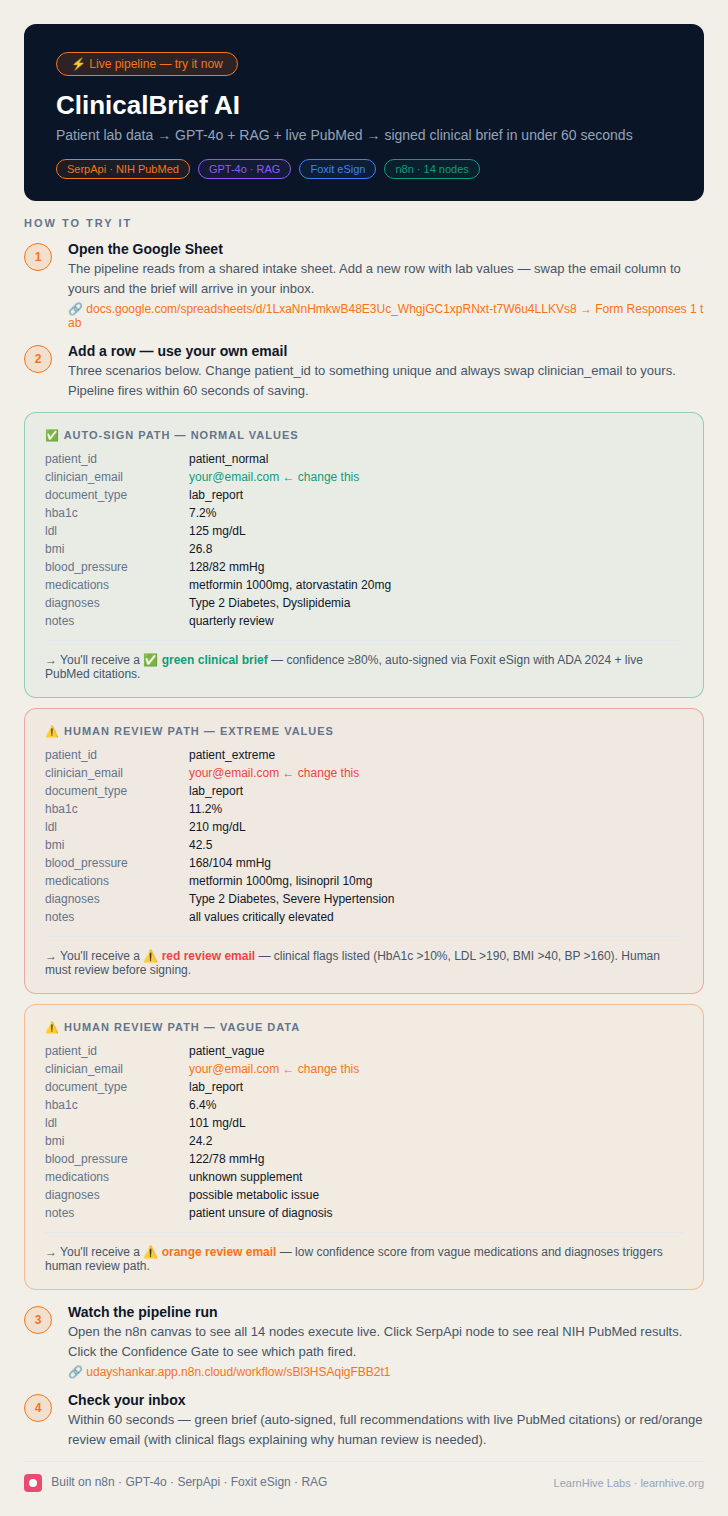
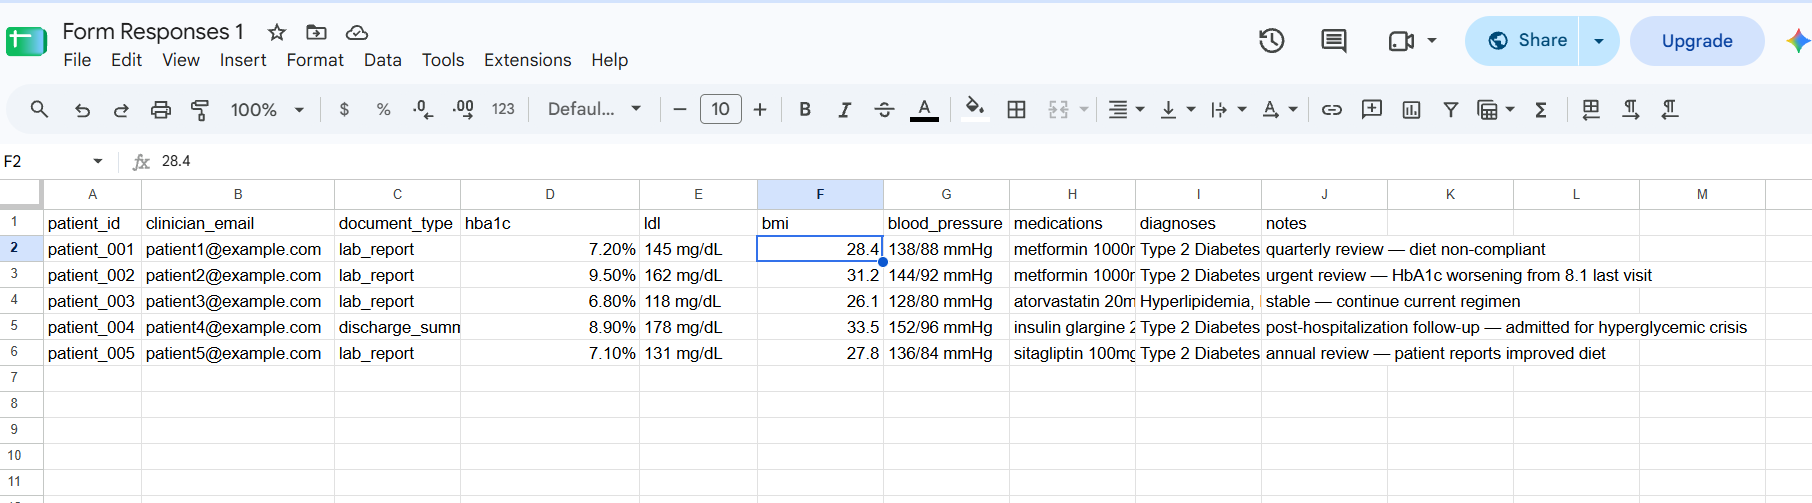
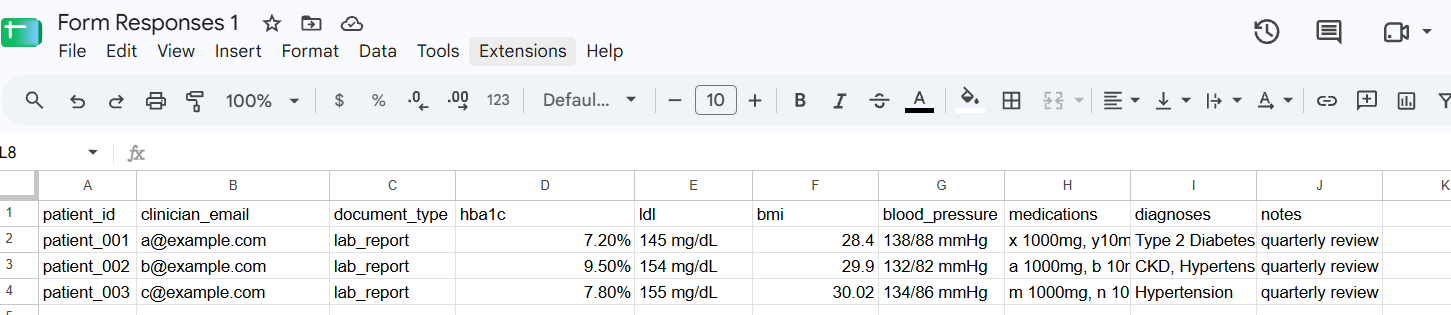
A patient or pharmacy staff member fills a Google Sheet with lab values — HbA1c, LDL, BMI, blood pressure, medications, diagnoses. No app. No login. No technical knowledge required.
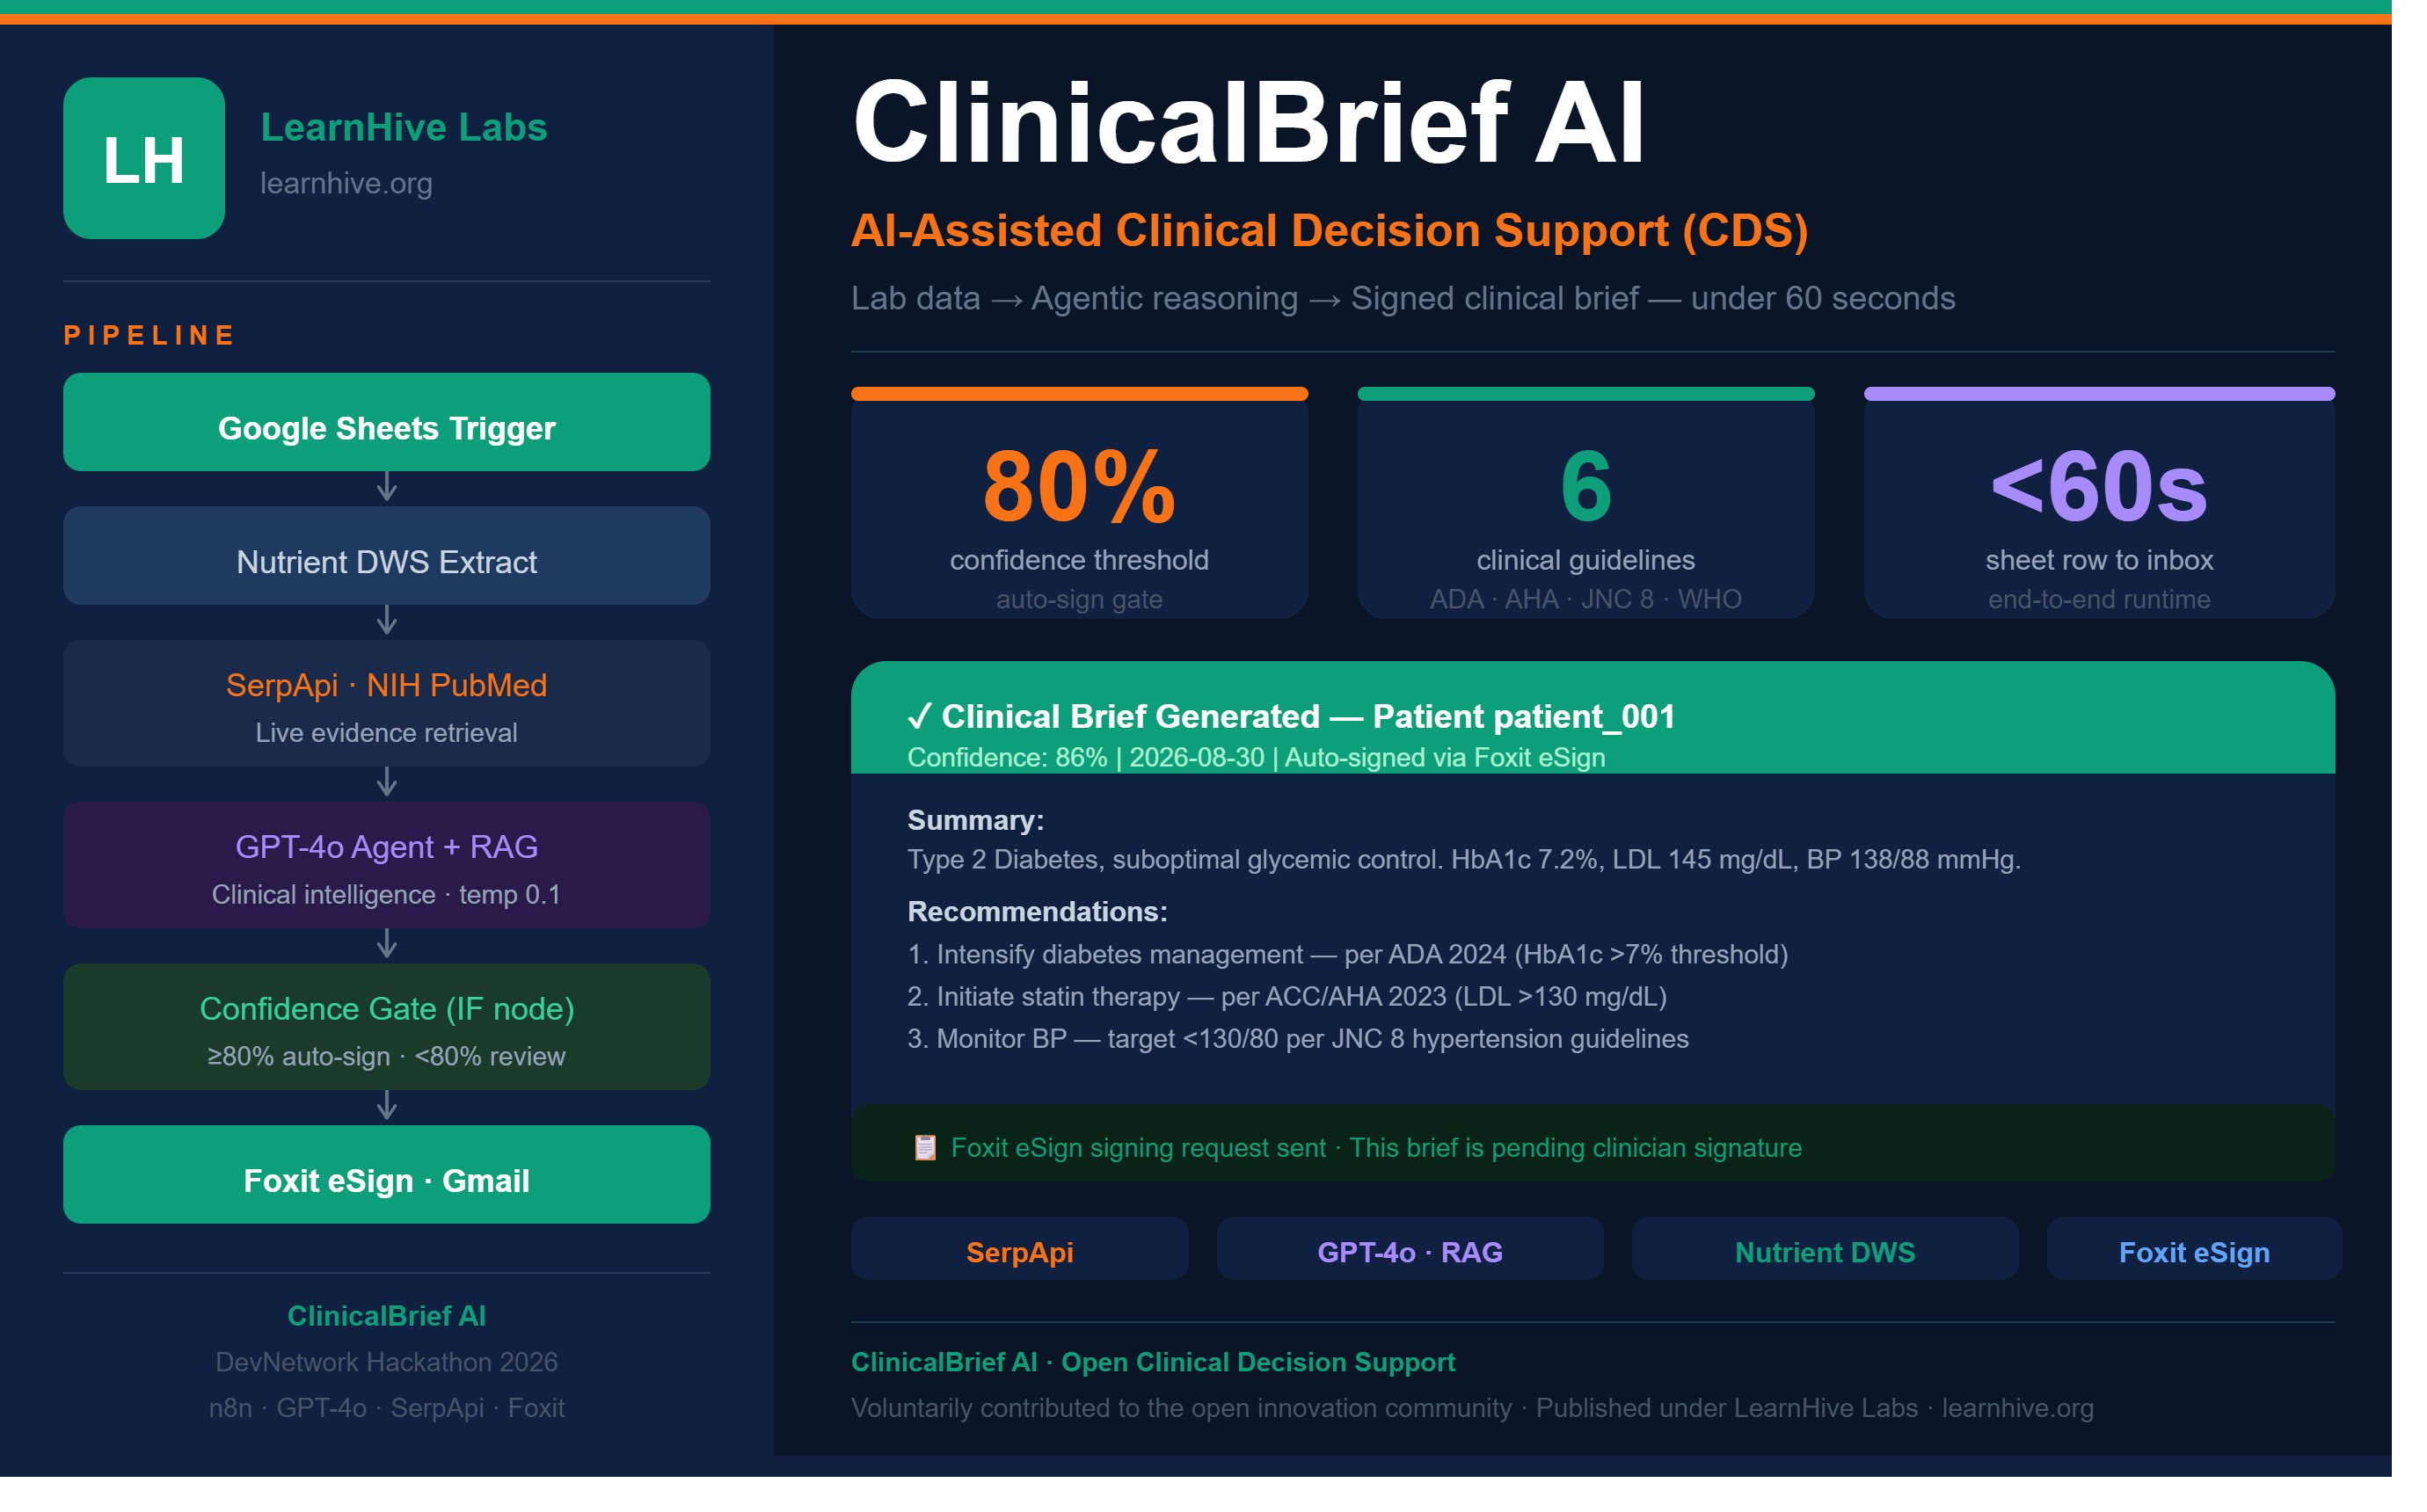
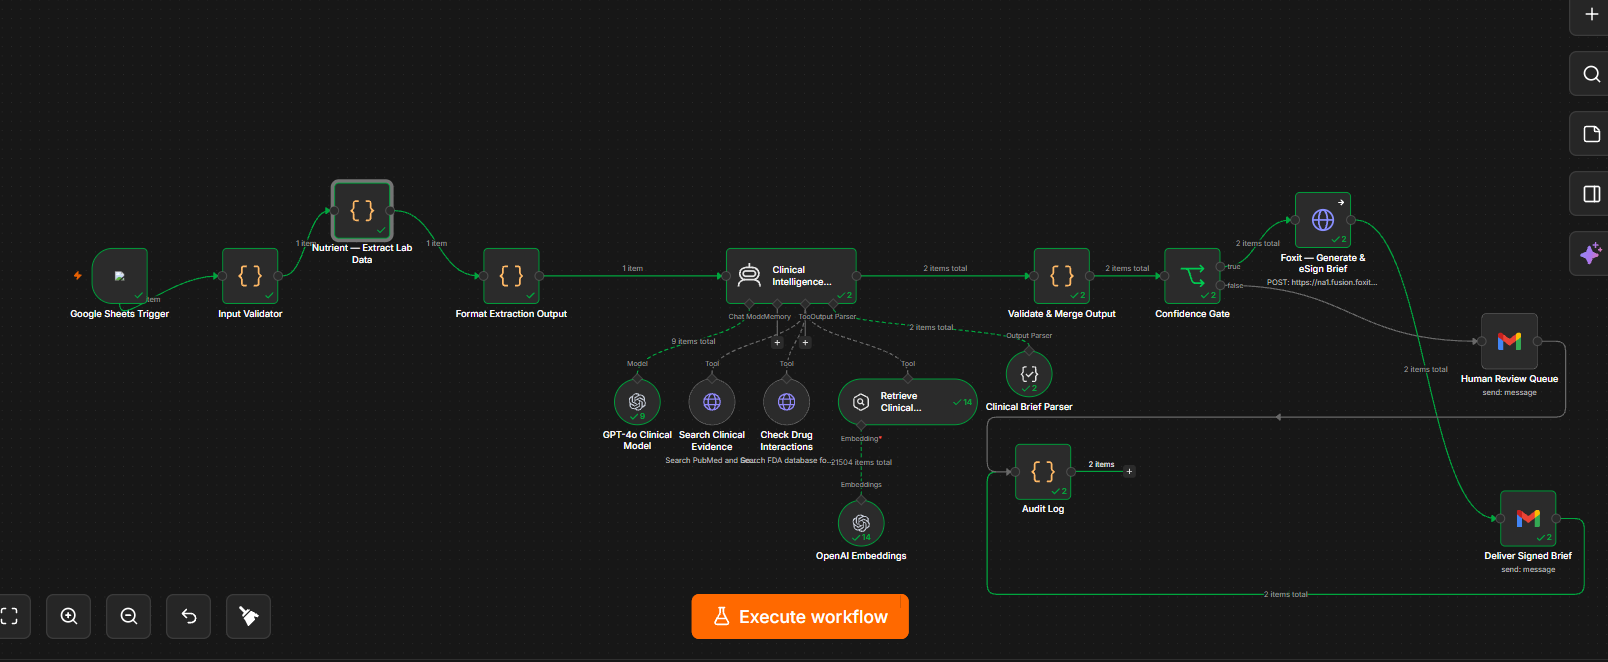
When a new row is added, the n8n pipeline fires automatically:
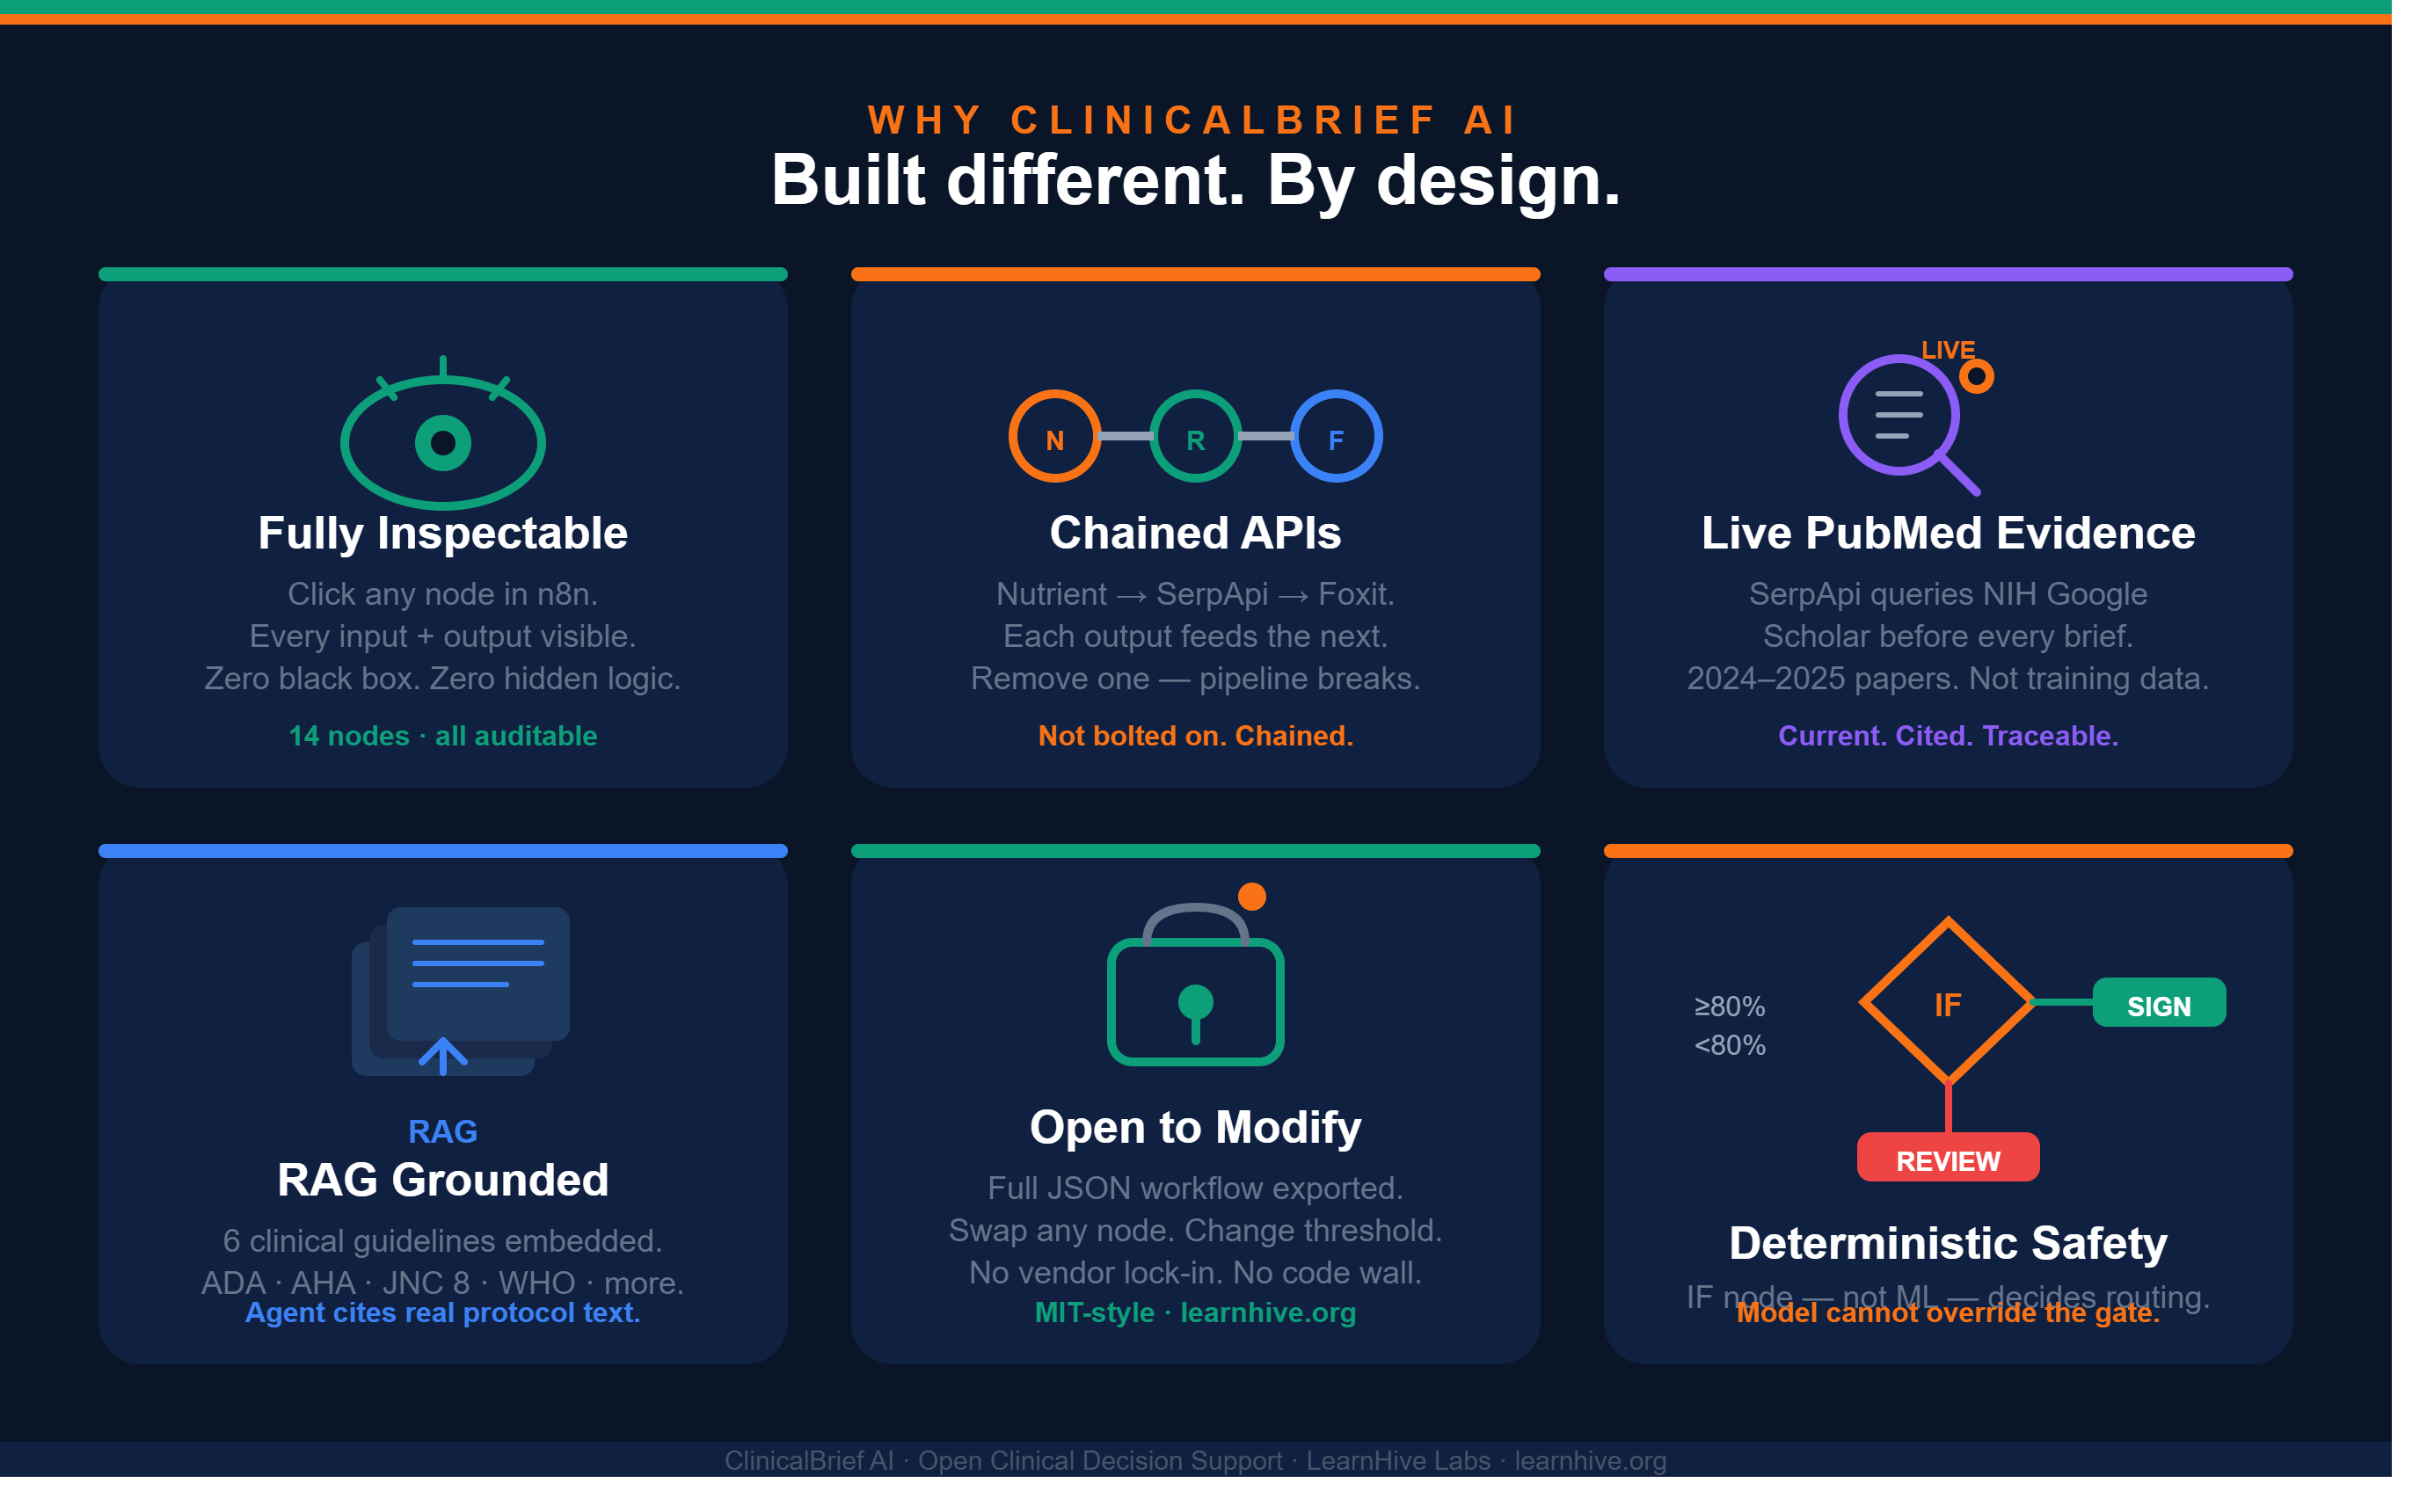
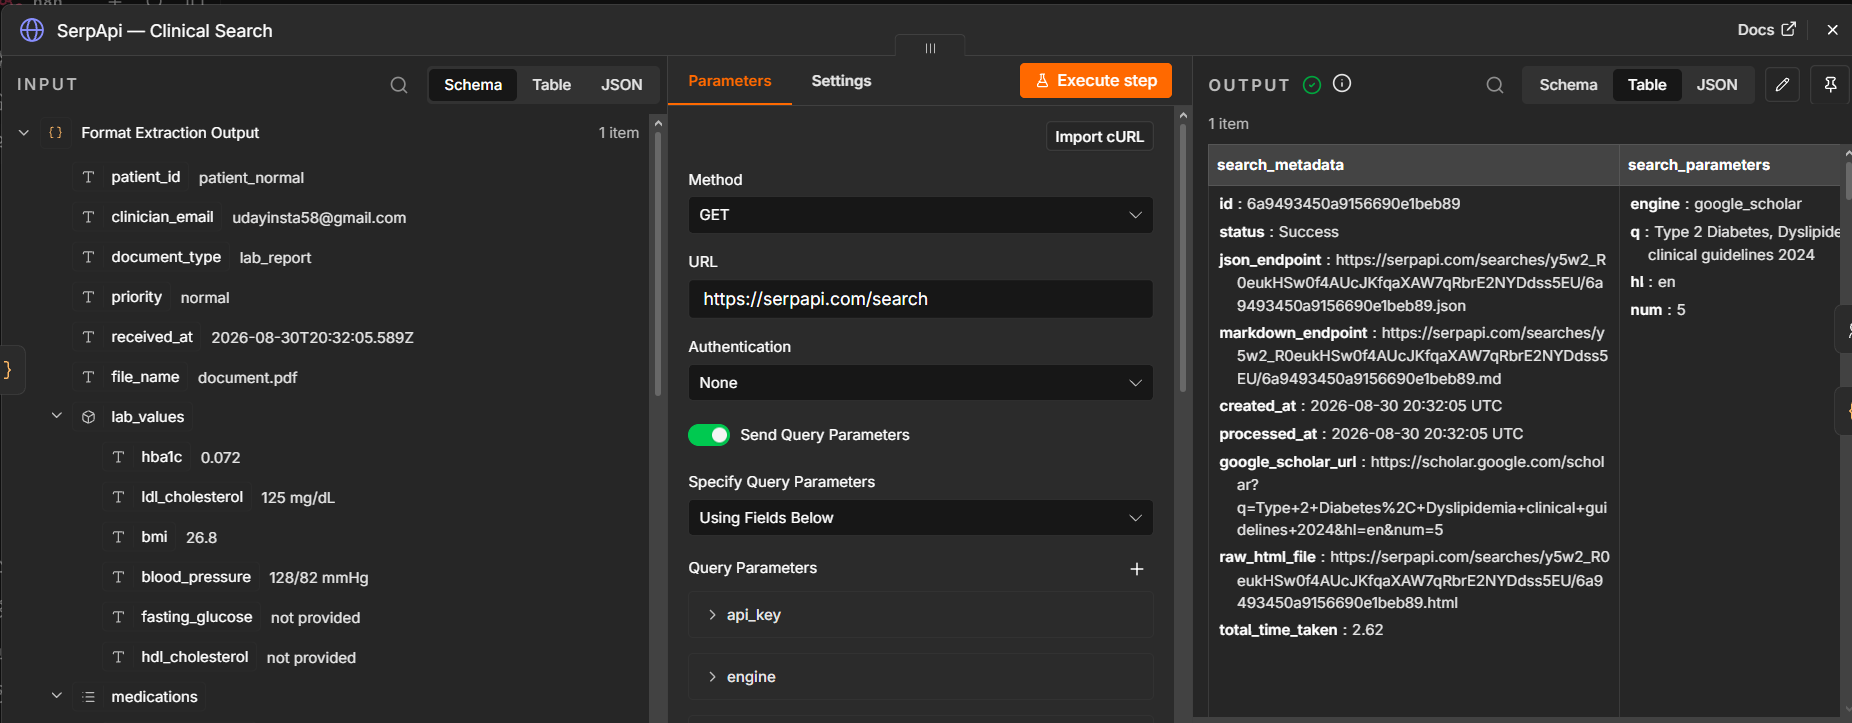
- SerpApi queries Google Scholar in real-time using the patient's diagnoses. Three current PubMed publications are retrieved and injected into the agent prompt before any generation happens.
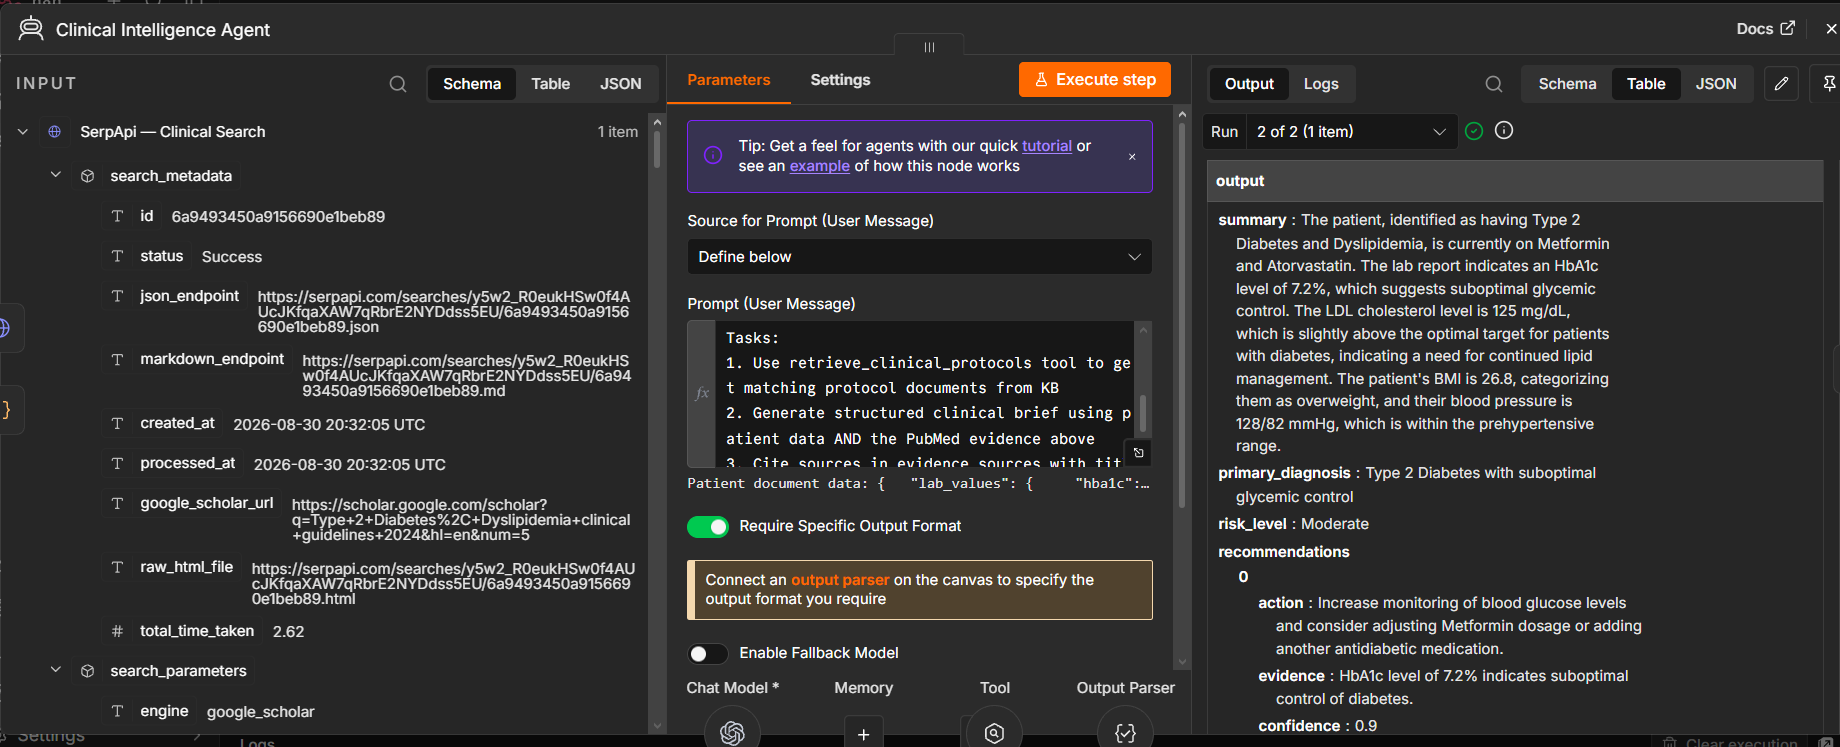
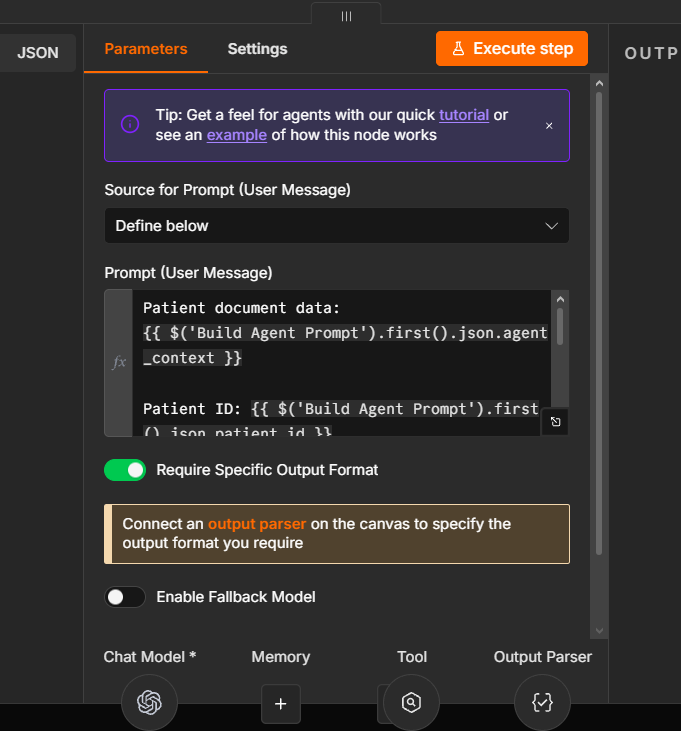
- GPT-4o receives the patient lab data + live PubMed evidence + RAG-retrieved clinical protocol guidelines (ADA 2024, ACC/AHA 2023, JNC 8, WHO, KDIGO, USPSTF). It generates a structured, source-cited clinical brief with a confidence score per recommendation.
- A Confidence Gate evaluates the combined score. At or above 80%: the brief is sent to Foxit eSign for electronic signature and delivered to the clinician. Below 80%: the full brief is routed to human review. No uncertain brief is ever auto-signed.
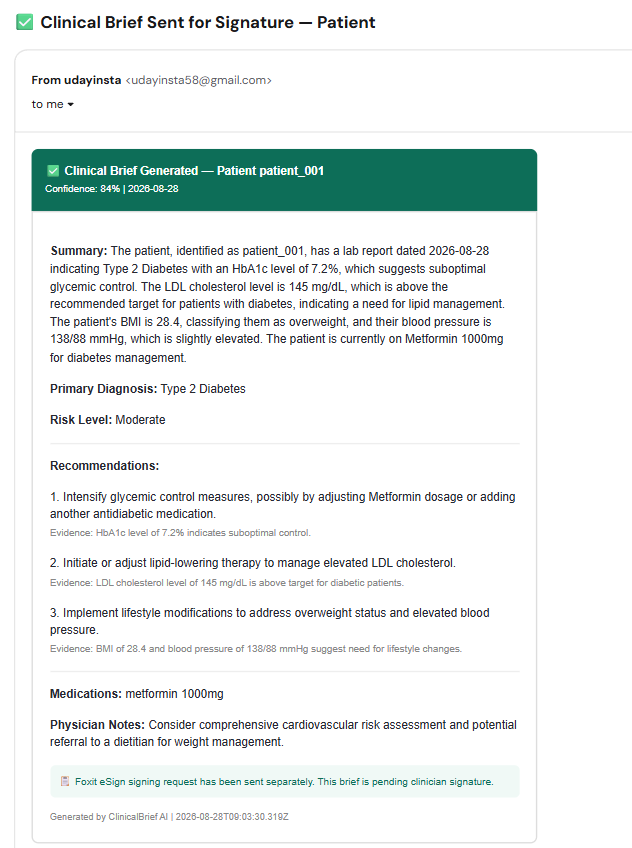
- The clinician receives an HTML email with the full summary, diagnosis, risk level, numbered recommendations with evidence citations, medications, and physician notes.
How I built it
Stack:
- n8n (cloud) — workflow orchestration, 14 nodes, fully visual and inspectable
- GPT-4o — clinical reasoning agent (temperature 0.1 for deterministic output)
- OpenAI text-embedding-3-small — 1,536-dimension embeddings for RAG
- SerpApi Google Scholar — real-time PubMed evidence retrieval
- Nutrient DWS — structured lab data extraction from patient documents
- Foxit eSign REST API — tamper-evident electronic signing
- Google Sheets — patient intake form (trigger)
- Gmail — clinical brief delivery
Confidence scoring:
Two independent scores averaged. Agent score comes from GPT-4o's self-assessment of evidence support. Extraction confidence comes from field-level scores on the lab data. Threshold: 0.80.
RAG knowledge base: 6 clinical protocol documents (ADA 2024, ACC/AHA 2023, JNC 8, WHO Metabolic Syndrome, NKF KDIGO 2023, USPSTF 2024) embedded and stored in n8n vector store. Agent retrieves top-3 matching passages per query using cosine similarity.
Challenges I ran into
- SerpApi as an agent tool —
toolHttpRequestinside the n8n agent node cannot execute. Fixed by moving SerpApi outside the agent as a regular HTTP node and injecting results into the prompt before the agent runs. - Foxit eSign sandbox endpoint — sandbox returns 404 on the standard envelope endpoint. Pipeline continues with
onError: continueRegularOutputso the rest of the workflow completes. Email delivery is unaffected. - In-memory RAG persistence — n8n's in-memory vector store resets on restart. Mitigated with a separate Seed KB workflow that re-loads all 6 documents before each session. Production fix: Supabase pgvector.
- Confidence routing — combining two heterogeneous confidence signals (agent self-report + extraction scores) into one routing decision required careful merging logic to avoid false positives in either direction.
Accomplishments that I'm proud of
- Full 14-node agentic pipeline running end-to-end — Google Sheets trigger to signed email delivery
- Real-time PubMed evidence retrieval via SerpApi integrated into every brief
- GPT-4o agent calling RAG tool autonomously (~7 tool calls per execution)
- Confidence-gated human-in-the-loop — deterministic routing, not a suggestion
- Three sponsor APIs chained meaningfully — each one's output is required by the next
- Fully inspectable in n8n — every node, every input, every output traceable
What I learned
Responsible clinical AI is not about the model — it is about the architecture around the model. The SerpApi integration taught me that live retrieval fundamentally changes output quality: the agent citing a 2024 ADA guideline with a real PubMed URL is categorically different from a model generating plausible-sounding advice from training data. The Foxit eSign integration reinforced the core design principle: the agent prepares the document, but a human authorises it. That boundary matters.
What's next for ClinicalBrief AI
- Real Nutrient DWS PDF extraction — replace simulated extraction with a real uploaded lab PDF processed by Nutrient's Data Extraction API
- Supabase pgvector — persistent RAG store, no reseed required on restart
- Foxit correct sandbox endpoint — verify and wire the signing flow end-to-end
- Multi-patient parallelism — n8n queue mode for concurrent executions
- Clinician dashboard — Google Sheets audit log → Looker Studio showing confidence trends, review rates, and turnaround times
- EHR integration — replace Google Sheets trigger with HL7 FHIR webhook
Built With
- ai
- api
- automation
- cds
- clinical
- clinicalbrief
- confidence
- decision
- embeddings
- esign
- evidence-based
- foxit
- gate
- gpt-4o
- healthcare
- human-in-the-loop
- learnhive
- medicine
- openai
- pubmed
- rag
- serpapi
- sheets
- support
- workflow

Log in or sign up for Devpost to join the conversation.